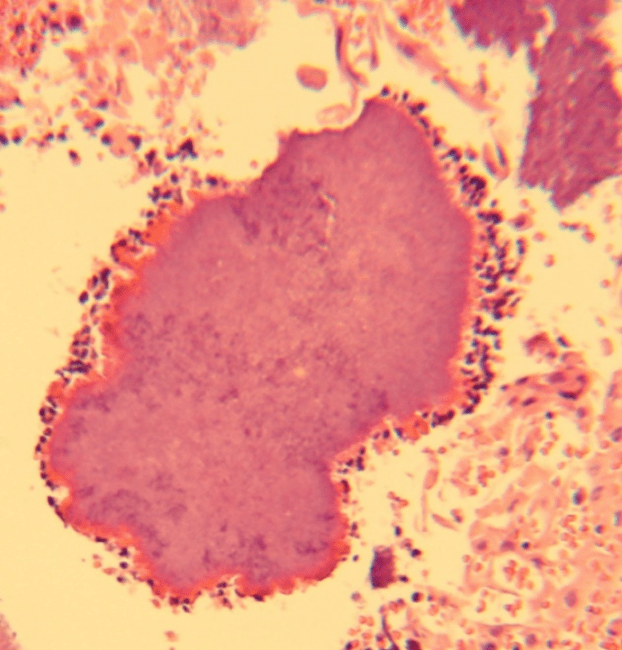
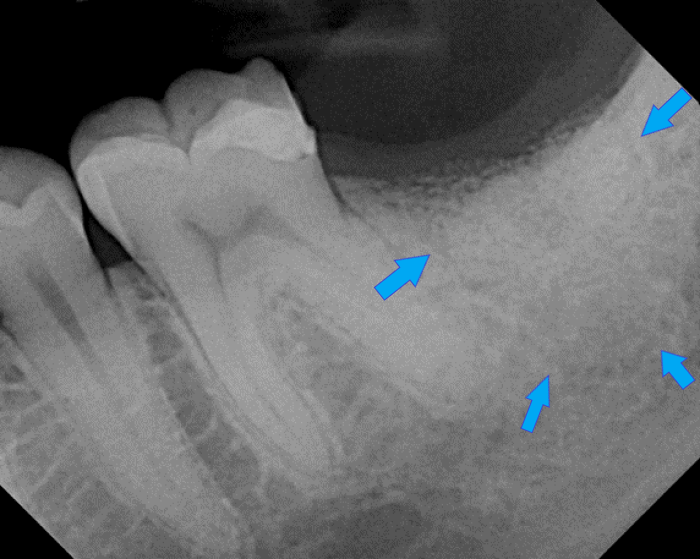
Cadaver bone grafts all have a very porous structure that makes the particles ideal for bacteria to colonize in an isolated environment, protected from both antibiotics and the host immune system.
Because of the propensity of cadaver bone grafts to become infected, dentists have developed aggressive decontamination methods to prevent cadaver bone graft infections. While there is no standardized method of post-extraction decontamination, most lecturers will have their own preferences for treating the extraction socket.
Due to the potential for infection, many clinicians who use cadaver bone grafts will choose to not graft an infected extraction socket at the time of extraction, but wait until the socket has time to resolve the infection prior to grafting. These clinicians are primarily those who are limited to the use of cadaver bone grafts and do not avail themselves to science-based grafts that are bacterially resistant. There is no reason for subjecting a patient to a second surgery to graft an infected socket. SteinerBio’s science-based bone grafts are bacterially resistant because our graft materials cannot be the nidus of an infection. By design, both SteinerBio granules and putties cannot be colonized by bacteria. The pore size on our βTCP granules is too small for bacterial colonization and our putties resist bacteria because bacteria cannot migrate into the graft.
A routine procedure after extraction is to use burs to remove granulation tissue and to perforate the socket wall to induce bleeding. However, any cutting, grinding, or scraping of bone kills the remaining cells to a depth on the remaining surface of bone. This fact is evidenced by the knowledge that after implant placement, the stability of the implant drops in the early weeks after implant placement. This decrease in stability is because the drilling of bone kills the cells on the surface of bone adjacent to the implant. Therefore, this bone then needs to be removed by osteoclastic resorption before osteoblasts can migrate to the implant and begin the integration process, thus resulting a decrease in implant stability. Dentists are taught that you must create bleeding in the socket to facilitate mineralization, but again, this is only when cadaver bone grafts are used. Vascular supply is necessary for cadaver bone graft mineralization to occur because cadaver bone grafts mineralize as a result of the inflammatory response to the foreign proteins in the cadaver graft and it is the vascular supply that transports the inflammatory cells.
The inflammation produced by the cadaver bone grafts uncouples normal bone formation where osteoblasts and osteoclasts work in unison to grow and remodel bone. This uncoupling of bone formation and resorption favors mineralization, but the bone that is produced is sclerotic and once formed, it never remodels.
The only way sclerotic bone remodels back into normal bone is when the source of inflammation is removed. In condensing osteitis, the sclerotic bone is present as long as the dental pulp is inflamed. If the pulp is removed, the sclerotic bone remodels back into normal bone. However, the source of sclerotic bone is never removed when an articular joint becomes sclerotic because the osteoarthritis is never resolved. Likewise, when cadaver bone grafts are placed, much of the cadaver bone graft remains in the site so that the sclerotic bone never converts back into normal bone.
So again, the grinding and drilling of the socket wall produces a surface of necrotic bone that is made to prevent post-operative infection and to supply blood that brings in cells of the immune system to produce mineralization when using cadaver bone grafts. None of this is necessary for science-based based bone grafts, and doing so kills the surface regenerative cells and fills the grafted site with blood that significantly delays normal bone formation.
Bone growing cells are never found in blood, blood clots, or healing granulation tissue. In order to prevent the delay of bone formation, blood, blood clots, and healing granulation tissue must be avoided. Some lecturers claim that the periodontal ligament (PDL) needs to be removed and also advise to scrape the socket wall to remove any remnants of the PDL. There is no scientific support for removing the PDL and by doing so, it only injures the socket wall, again, delaying bone formation.
After physically drilling, grinding, and scarping the socket wall, many professors and lectures advise applying antimicrobial therapy to kill residual bacteria. For example, the clinically used concentration of CHX (2%) permanently halts cell migration and significantly reduces survival of fibroblasts, myoblasts, and osteoblasts.
Low pH solutions decrease cell viability and induce cell death in osteoblasts. Viability of osteoblastic cell line, MC3T3-E1, was markedly influenced by the acidity of the culture media in which they are grown. Both pH values of 6.4 and 6.8 induced a significant decrease in cell viability compared with that of pH 7.4 (P < 0.05). Meanwhile, all cells died when cultured in media at pH 6.0.
The pH of betadine is 4.2. Applying betadine to bone will cause significant cell death.
A common antimicrobial for an infected socket is powdered tetracycline. The pH of 1% tetracycline is 2.0. A powdered solution of tetracycline will have an even lower pH and will be toxic to any bone cells. In addition, tetracycline makes no sense as a one-time antimicrobial because it does not kill the bacteria, but stops replication. Stopping replication of the bacteria will not be effective as a one-time application. The only possible benefit of applying a concentrated solution of tetracycline is that it is so toxic with the low pH that it will kill bacteria at the same time it kills all the surrounding bone cells.
Gentamycin is another common antibiotic recommended for socket application. Gentamicin is a clear, colorless solution, having pH ranging from 3.0 to 5.5. At this pH, it is obviously toxic to bone cells.
If the clinician feels compelled to apply an antibiotic to bone, they should use an antibiotic that is made for IM or IV use. These solutions are buffered and avoid the low pH of most of these medications.
Laser application to the bone of an extraction socket is a common recommendation. If the laser is set to a level of intensity designed to stimulate bone formation, it will not be intense enough to kill bacteria. If the laser is set to an intensity designed to kill bacteria, it will also kill bone cells.
So, drilling and grinding bone kills surface bone cells and the application of toxic medications can penetrate to kill an even deeper layer of bone cells. This therapy is advised for cadaver bone grafts because it is effective in killing bacteria and preventing infection. In addition, it does not significantly slow the mineralization process because with cadaver bone grafts, the mineralization process is dependent upon the inflammatory response and is not limited to the production of bone by way of migrating osteoblasts.
What is advised for cadaver bone does not translate to science-based bone grafts. Science-based bone grafts require an inflammation-free environment for bone formation. In addition, science-based bone grafts relay only on viable osteoblasts and their progenitors to form bone. The treatment advised for cadaver bone graft sockets kills off these cells and the area of damaged bone then needs to be removed by osteoclasts before bone formation can occur. The scenario is the same for implant integration. The drilling of bone damages the surface bone cells that now need to be removed before integration can begin. Simple drilling for implants only kills the very surface cells, but when you drill and scrape aggressively and then apply chemicals that penetrate and kill cells to a certain depth, a great deal of resorption, remodeling, and regeneration needs to occur in the damaged bone before bone regeneration can occur in the grafted socket.
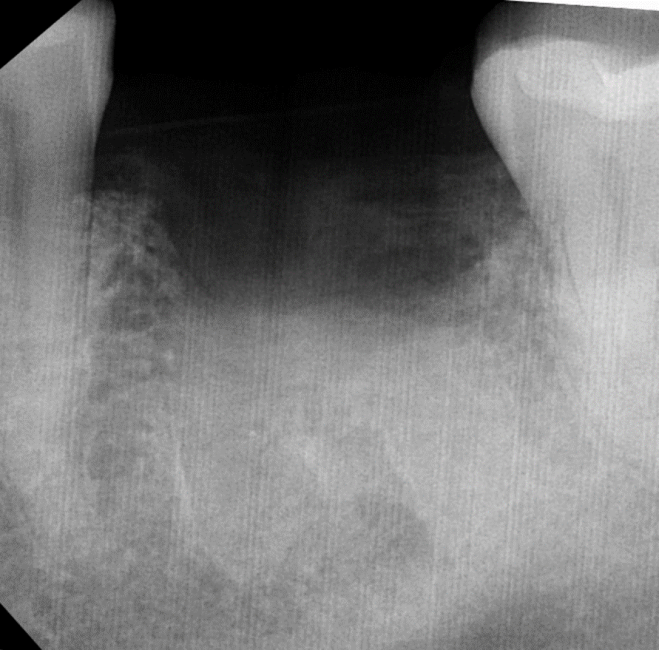
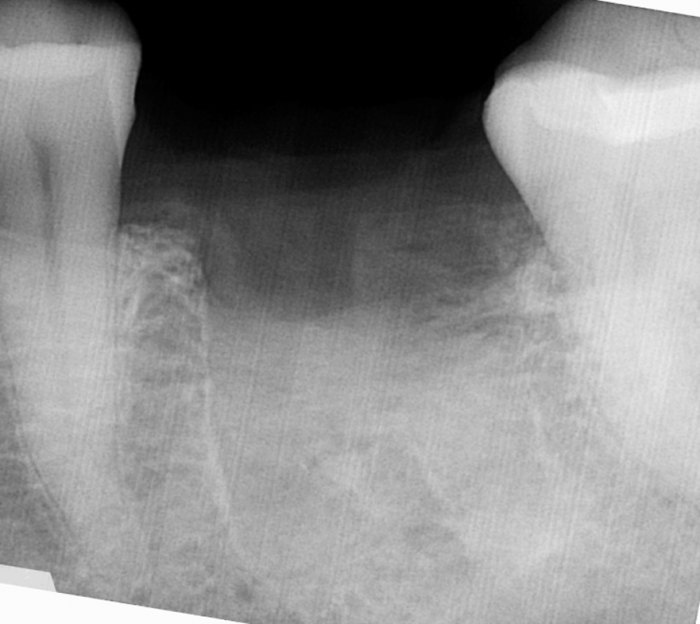
With this knowledge we can now move on to the subject of this post. When using cadaver bone grafts, aggressive socket treatment does not interfere with mineralization and prevents bone graft infections, but aggressive socket treatment produces bone graft failure and produces delayed post extraction pain when using SteinerBio science-based bone grafts.
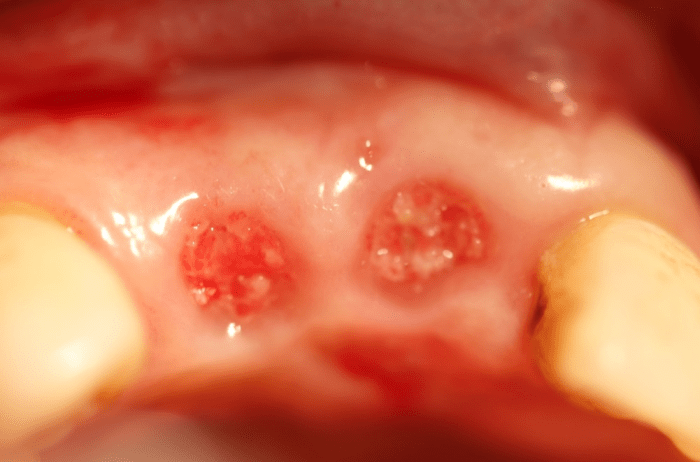
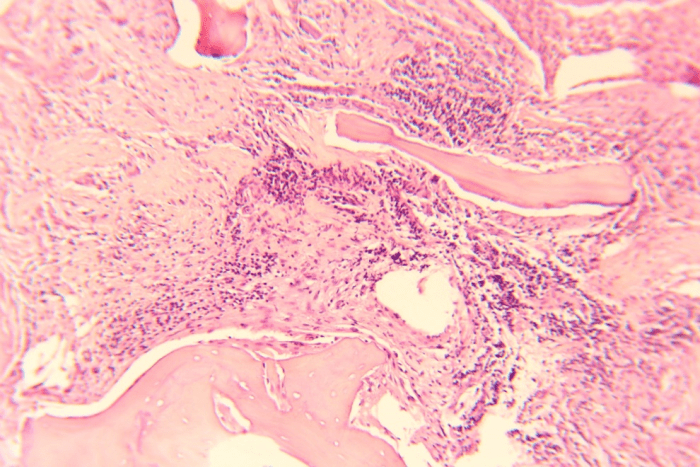
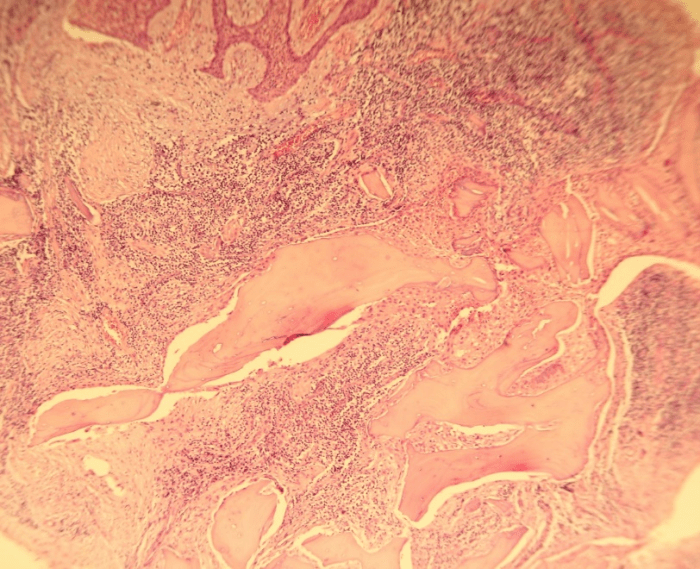
Let’s look at a few cases to understand this concept.