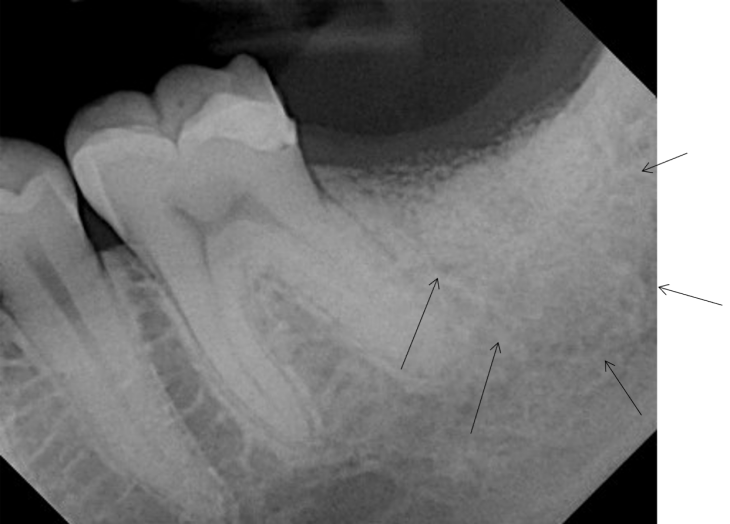
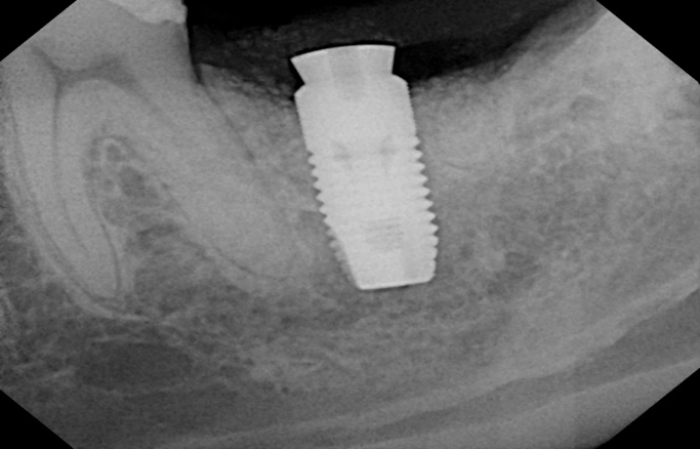
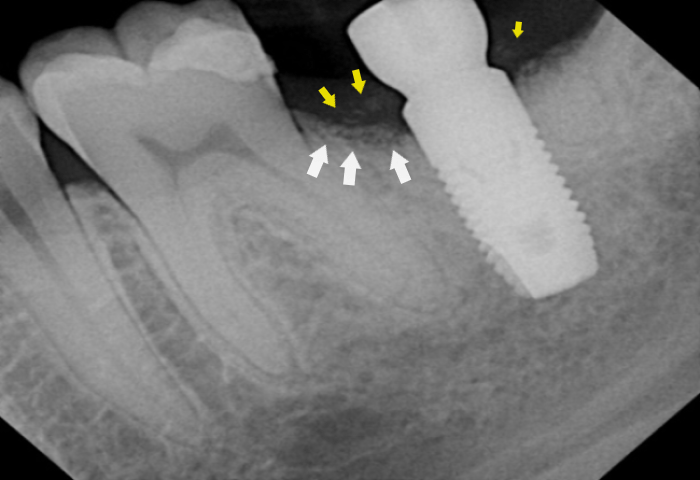
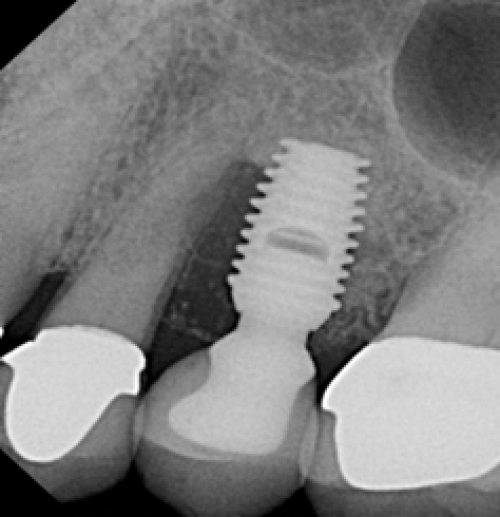
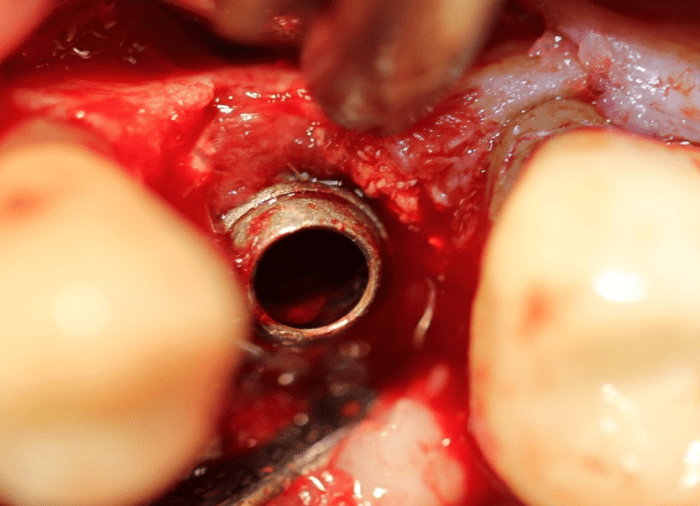
Bone chips are seen floating in the granulation tissue. In periimplantitis and periodontitis, bone resorption occurs ahead of the infection and bone is never found in the granulation tissue. Therefore, the bone loss in this case is not caused by periimplantitis. The diagnosis in this case in not periimplantitis but bone graft failure.
We have no studies that have evaluated the long-term success rates of implants placed in sockets grafted with Bio-Oss or allograft, so we have no scientific basis for placing implants in sockets grafted with these materials. We know that cadaver bone graft materials produce marginal bone loss. We know that cadaver bone grafts are the variable that causes early implant failure. While no one has ever published data on the long term success rates of implants placed in sockets grafted with Bio-Oss or allografts, we know that a high percentage of implant loss occurs in sites grafted with cadaver bone grafts. Clinical observation indicates that more implants are lost that are placed in sockets grafted with cadaver bone grafts than as a result of periimplantitis.
Studies with cadaver bone grafts seldom have no graft as a control. When cadaver bone grafts are compared to no graft, the findings are that cadaver bone grafts produce less mineralization than no graft, so they actually inhibit bone formation. But it gets worse. A recent study performed at Harvard and a university in Israel compared MFDBA and a collagen membrane with a collagen bone graft product to assess their effectiveness of the two materials in ridge augmentation surgery. Everything was done to ensure a successful outcome. They excluded patients with any reason to produce anything other than ideal results. The ridge augmentations were mainly in areas bordered by teeth which are very simple to augment. The study was very well done. After 9 months, as expected, the collagen graft failed completely, producing no increase in ridge width. Anyone who follows our posts knows that collagen should never be placed in or over a bone graft. However, what makes the study interesting is that the MFDBA covered with a collagen membrane completely failed also. In the MFDBA membrane group, at 2 mm below the crest there was a gain of 0.38 mm; at 5 mm below the crest there was a gain of 0.27 mm; at 8 mm below the crest there was a loss of -0.34 mm of bone width. The authors spent the entire article trying to cover for complete failure of the cadaver bone graft.
Typically, a study that blows up the established paradigm would never be published, but in this case the authors had no option but to publish the results because the study was posted on ClinicalTrials.gov prior to initiation of the study. Many journals and academic institutions require a clinical study to be posted on clinicaltrials.gov because this forces the authors to publish their results without modification to suit their bias. In this case, the university authors were forced to publish results that contradicts what they teach you to do to your patients. The company that paid for the collagen graft to be studied surely would have never wanted this study published either.
Cadaver bone grafts are never resorbed and produce sclerotic bone that does not integrate to the implant surface. Only normal bone has a high implant success rate and only fully resorbable synthetic bone grafts that produce normal bone that can integrate to the implant have the potential for long term success.
Cadaver bone grafts are researched and taught in all US dental schools. Most all lecturers promote their use in various clinical applications. Cadaver bone graft material is the paradigm in the United States, so its effectiveness cannot be questioned. If you do a ridge augmentation using a cadaver bone graft and it fails, the problem is either the operator or the patient because the paradigm teaches you that it cannot be the material that fails. In dentistry, the cadaver bone graft paradigm teaches that it is the best possible bone graft and as a result, research into bone and bone graft biology has not occurred, reflecting the damage a paradigm can do to a profession. It is instructive to read what Max Planck said about scientific paradigms: “A new scientific truth does not triumph by convincing its opponents and making them see the light, but rather because its opponents eventually die, and a new generation grows up that is familiar with it.”