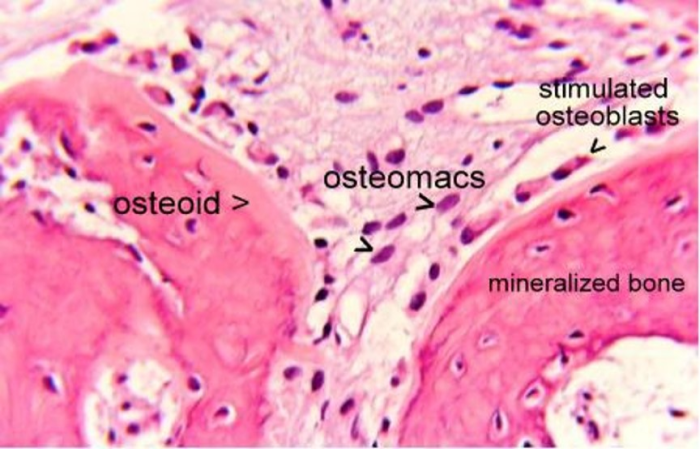
The immune system plays a critical role in determining the success or failure of bone regeneration. Trauma, infection, thermal, or chemical injury results in an immediate, non-antigen specific immune response. This response is controlled by cells of the innate immune system and is called acute inflammation. Acute inflammation is the first stage of healing and is intended to remove the cause of the injury, remove any damaged tissue, and set the stage for the regenerative process to restore normal form and function.
The process of acute inflammation is initiated by resident immune cells already present in the involved tissue, mainly resident macrophages, dendritic cells, histiocytes, Kupffer cells, and mast cells. These cells possess surface receptors known as pattern recognition receptors, which recognize two sub-classes of molecules: pathogen-associated molecular patterns (PAMPs) and damage-associated molecular patterns (DAMPs). PAMPs are compounds that are associated with various pathogens, but which are distinguishable from host molecules. DAMPs are compounds that are associated with host-related injury and cell damage. The mediator molecules also alter the blood vessels to permit the migration of leukocytes, mainly neutrophils, and macrophages, outside of the blood vessels into the tissue.
Acute inflammation requires the production of pro-inflammatory substances such as cytokines. These may include tumor necrosis factor-alpha (TNFα), Interleukin 1 beta (IL1β), IL-6, IL-8, and chemokines such as macrophage chemotactic protein 1 (MCP-1) and reactive oxygen intermediates (iNOS).
Together these cells and molecules eradicate microbes or toxins, remove damaged tissue, and recruit more cells to begin the regenerative phase. The acute inflammatory phase is guided by M1 macrophages of the innate immune system.
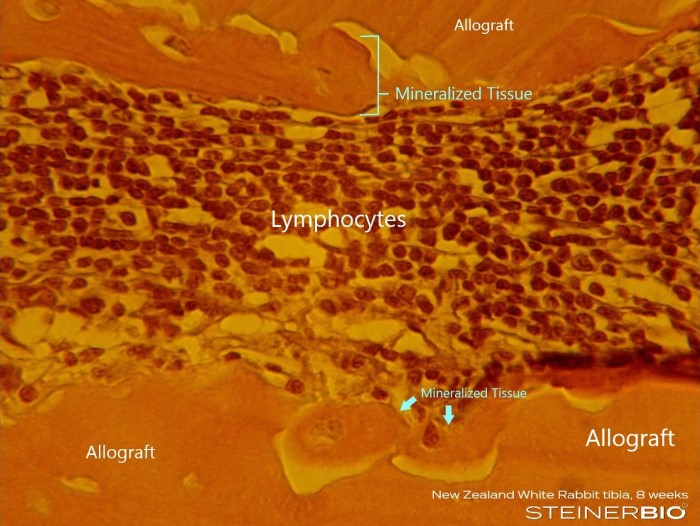
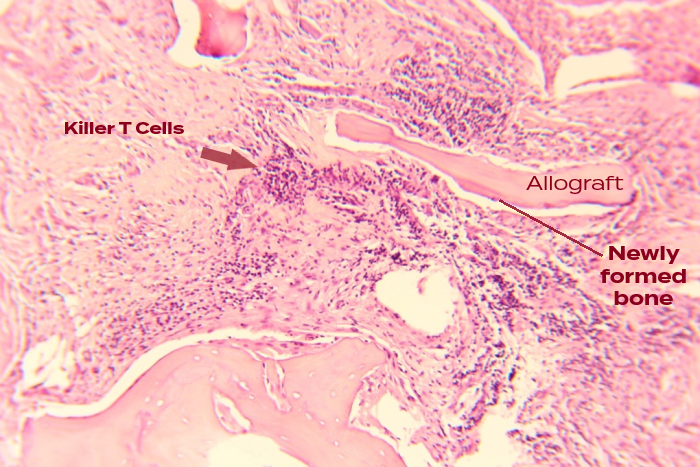
When the acute inflammatory response has removed the offending agent and cleared the damaged tissue, the pro-inflammatory M1 macrophages are polarized into anti-inflammatory M2 macrophages. M2 macrophages produce Interleukin 10 (IL-10), IL-1 receptor antagonist (IL-1ra), and Transforming Growth Factor beta (TGFβ), and subsequently direct regeneration that restores normal form and function. However, if acute inflammation is not able to eradicate the cause of the injury in a timely manner, chronic inflammation develops and regeneration is blocked. In chronic inflammation, the primary immune cells are M1 macrophages and T lymphocytes, which produce cytokines and enzymes that cause more lasting damage to local cells and tissues. In chronic inflammation, resolution of the acute infection gives way to ongoing tissue damage and destruction, manifesting as tissue fibrosis in soft tissue and sclerosis in bone.
With this knowledge we can discuss and understand why some bone grafting materials produce regeneration and why other bone grafting material produces fibrosis and sclerosis.
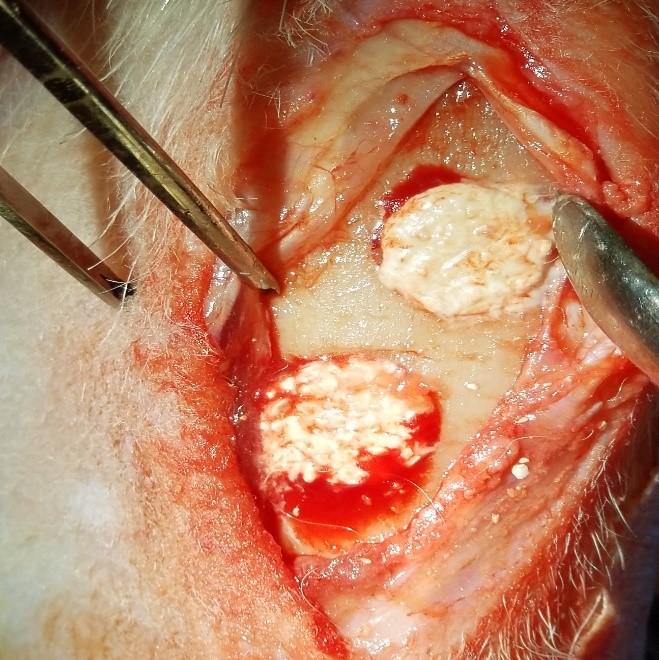
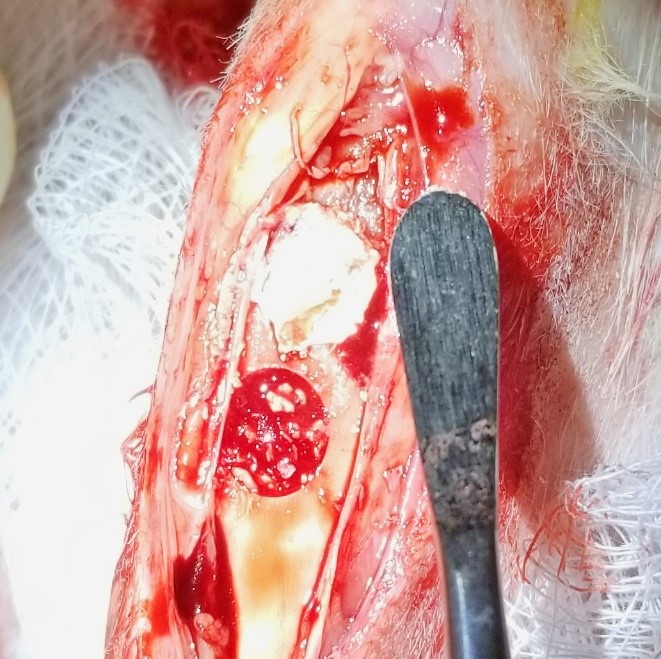
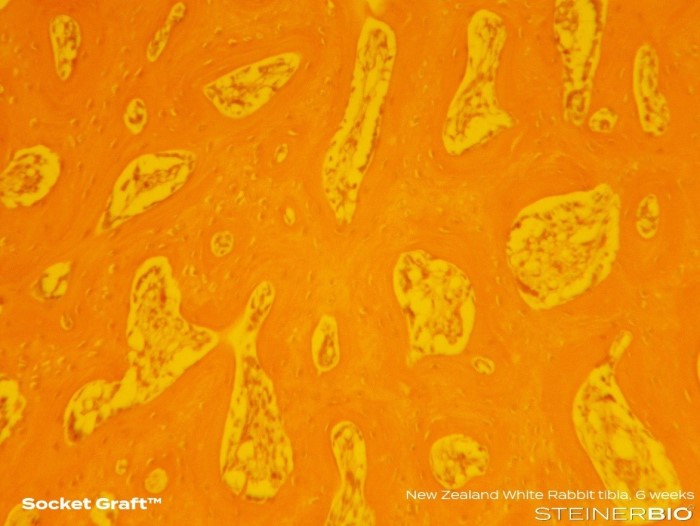
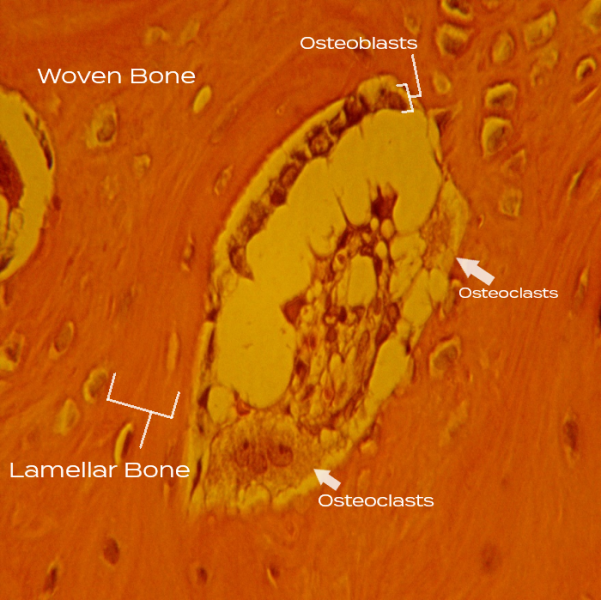
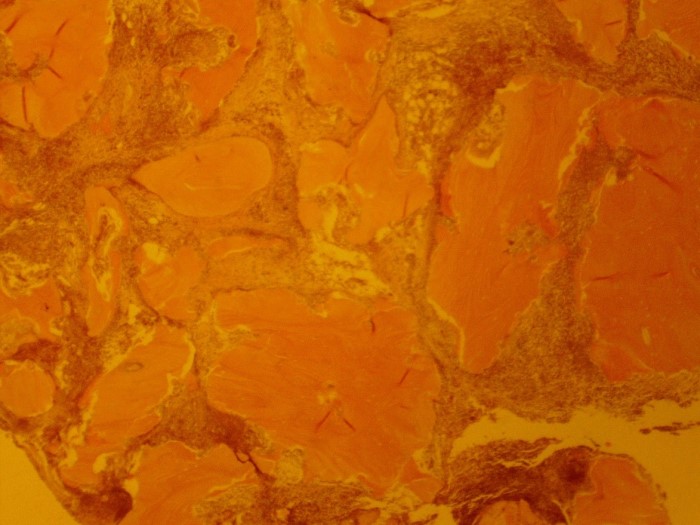
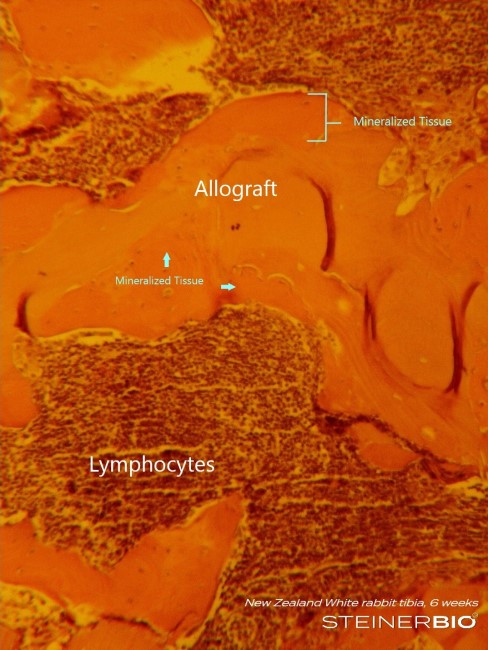
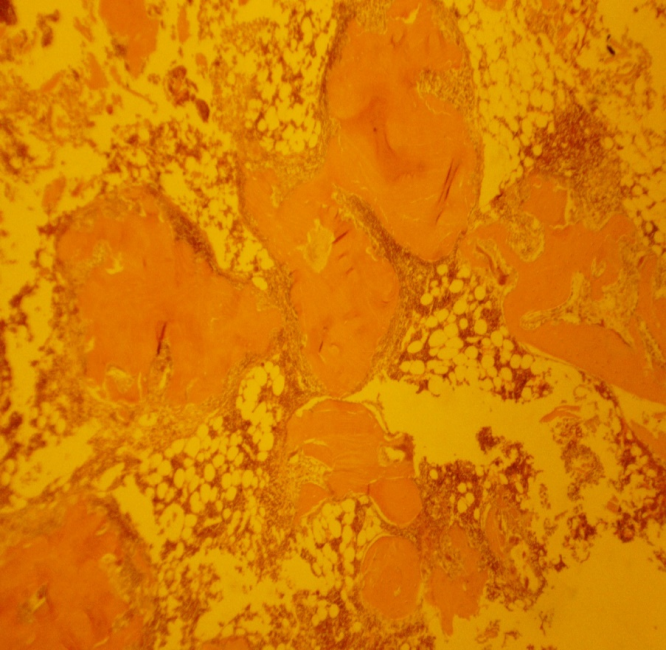
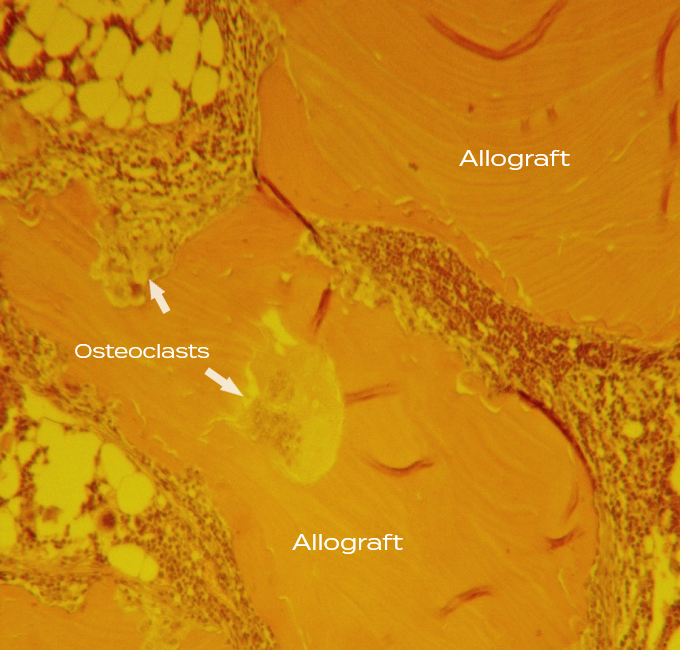
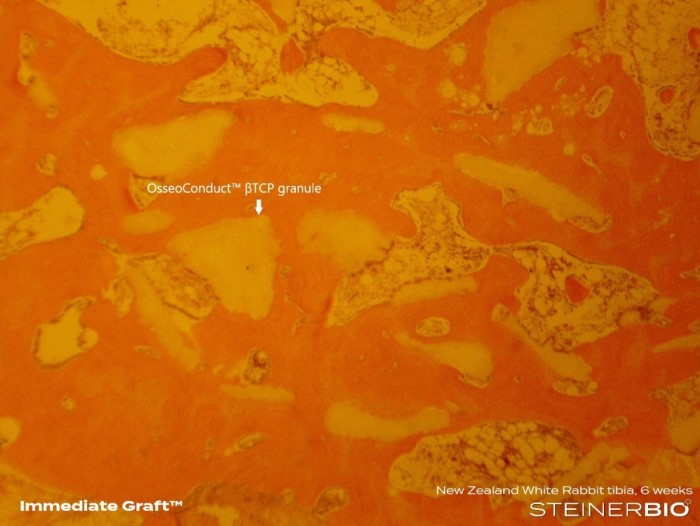
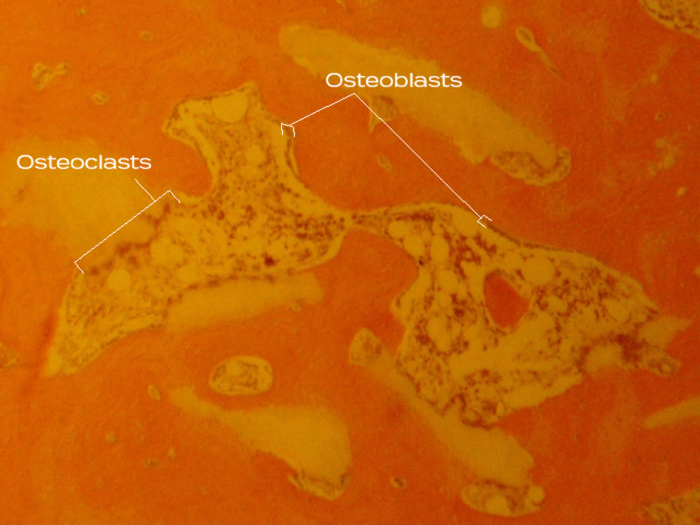
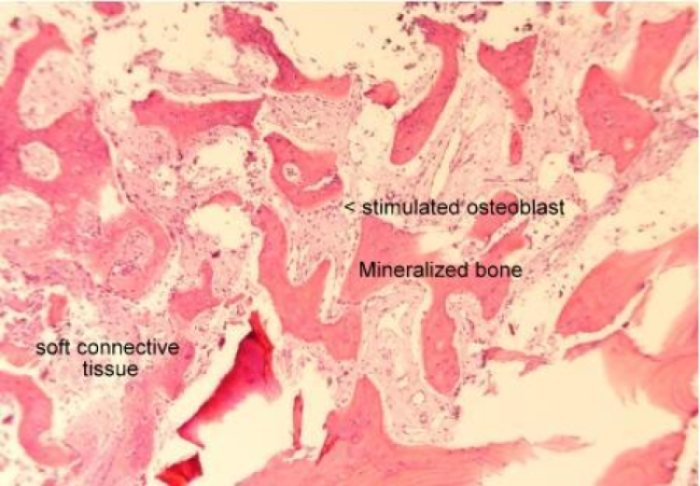
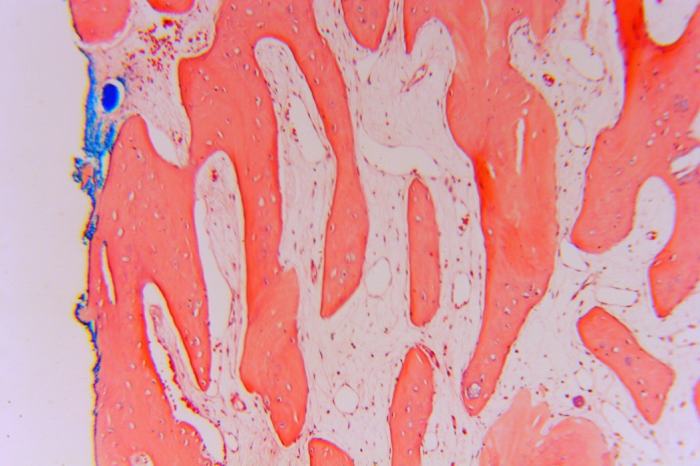
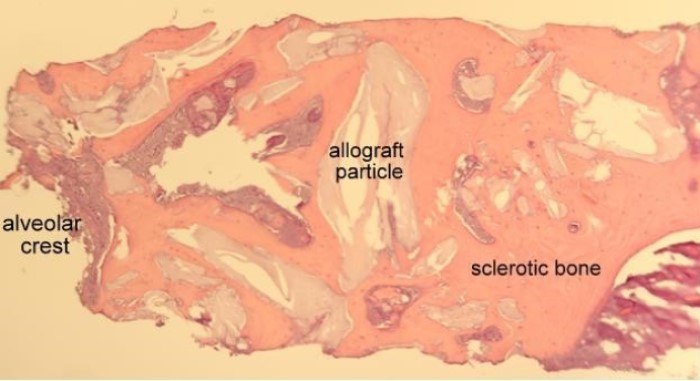
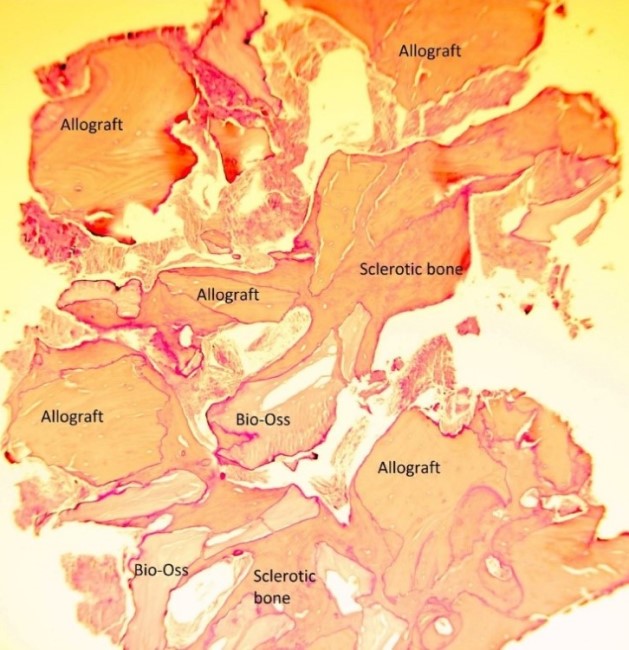
In histologic studies of bone, virtually all bone samples are taken with a trephine prior to implant placement. Dentistry makes the assumption that after loading, the bone graft particles will be resorbed and mature lamellar bone will support the implant. However, dentistry has no scientific support for this assumption and not knowing what type of bone is produced after loading can make the difference between implant success or implant loss. In order to ascertain the type of bone that forms under load, we studied bone histology in a rabbit tibia model. Bone grafts placed into rabbit tibia will gradually become loaded as the bone grows and the animal puts load while walking and supporting itself.