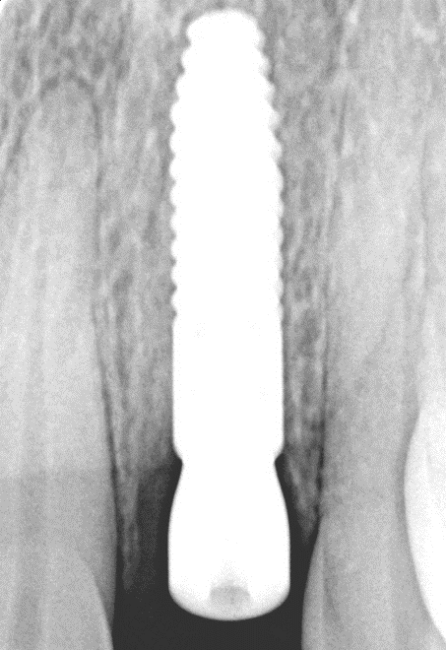
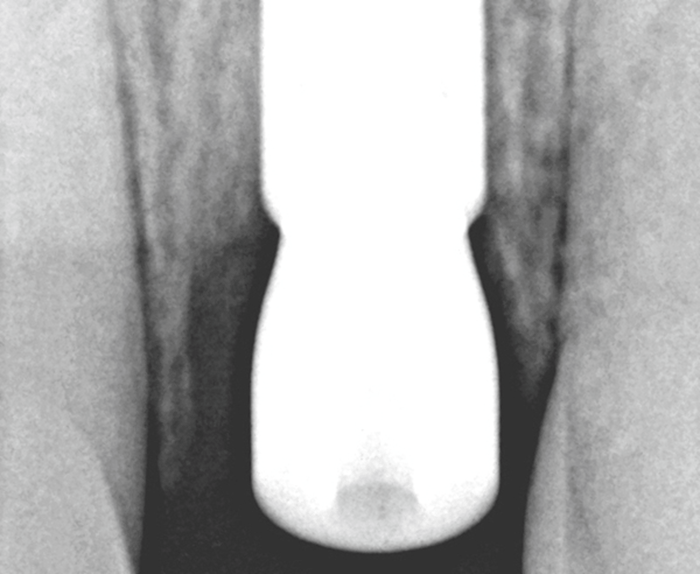
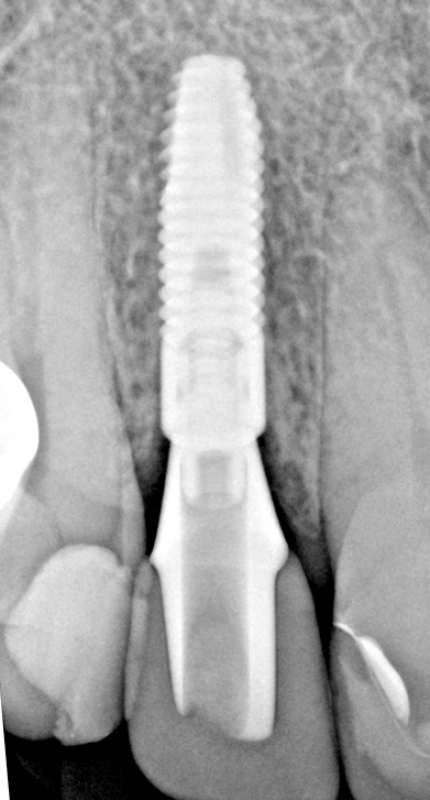
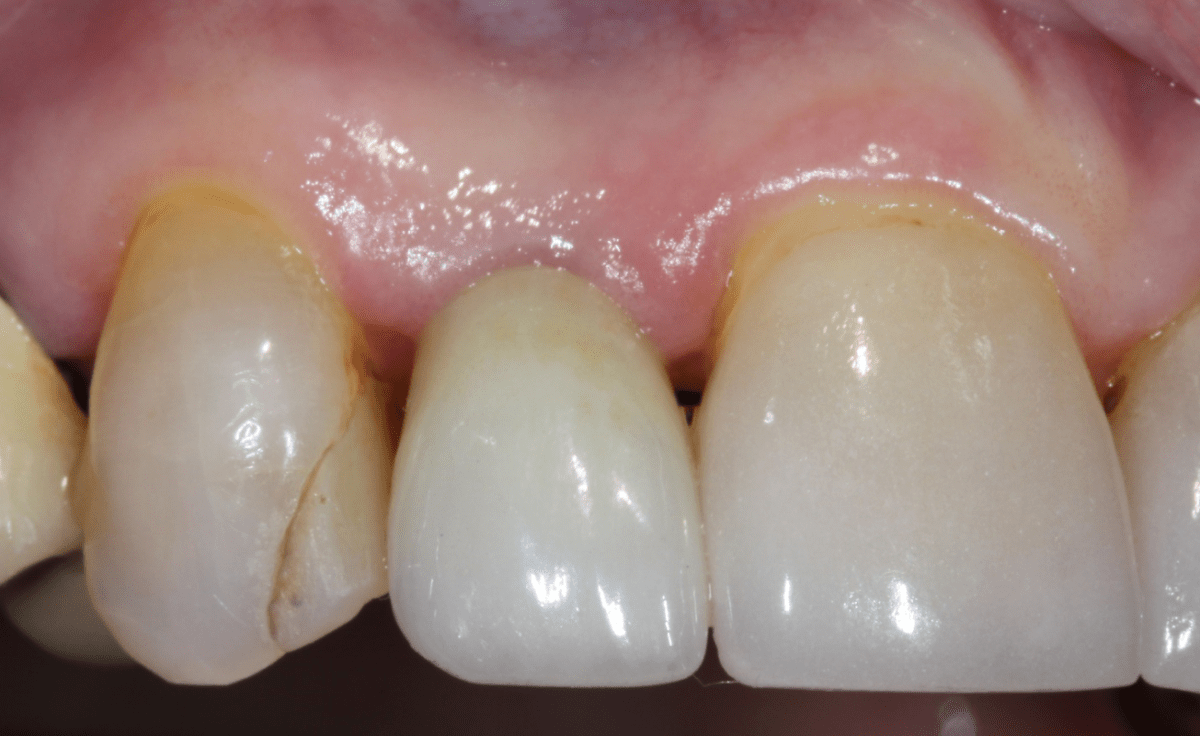
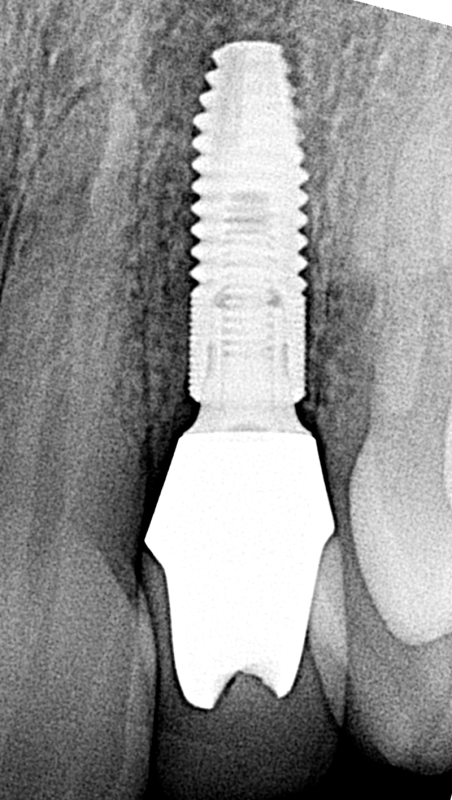
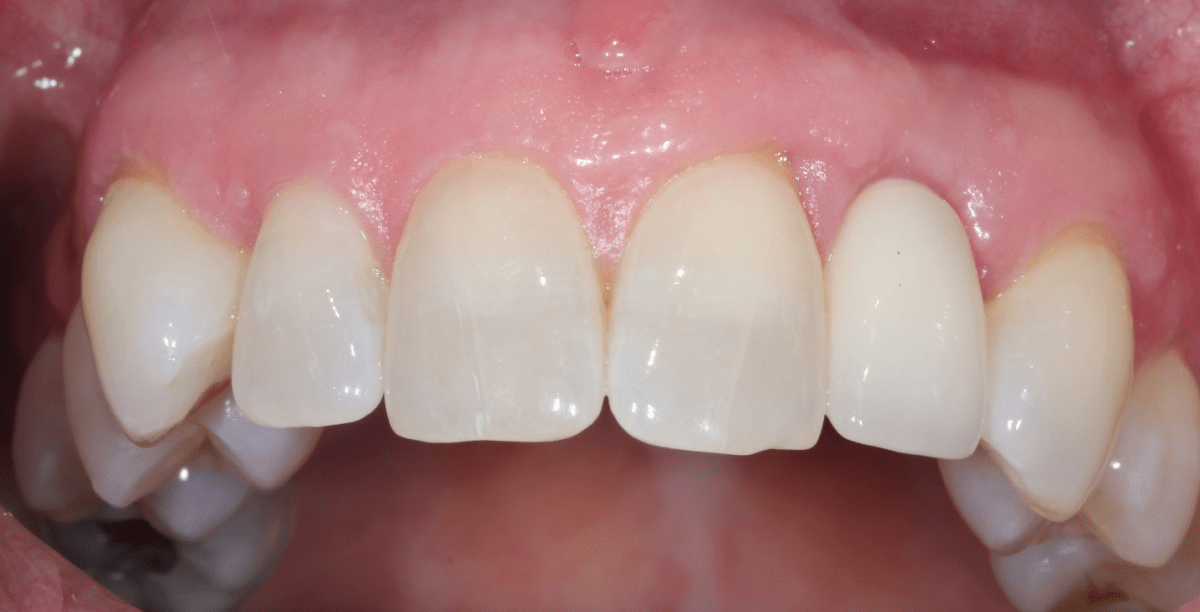
The goal of any implant method is to produce 100% bone to implant integration with normal bone that will last the life of the patient. Because there is something mineralized on the radiograph does not ensure that the tissue is normal bone and does not ensure it is integrated to the implant. If what you see on a radiograph is anything other than normal bone integrated to the implant surface, the health of the tissue and the longevity of the implant is in doubt.
The ability to produce normal bone integrated to the implant surface requires the presence of osteoblasts or the regenerative cells that produce osteoblasts. The vast majority of these cells are located in the apical area of the alveolar ridge where a large amount of cancellous bone exists. Comparatively, there are very few osteoblasts or regenerative cells found in the narrow bony septum that separate teeth.
In an extraction socket, the vast majority of bone formation is produced by cells that migrate from the apical region of the socket and this is the reason that the last area to mineralize in an extraction socket is the center of the alveolar crest.
The problem with immediate implants is that with the implant in place, the vast majority of bone forming cells are blocked from mineralizing the crest, which can result in bony defects around the coronal area of the implant. The only way to know if you have produced normal bone around an immediate implant is to use a resorbable synthetic.
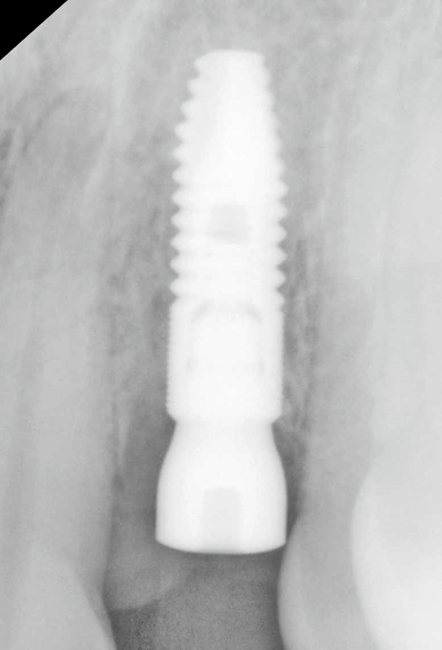
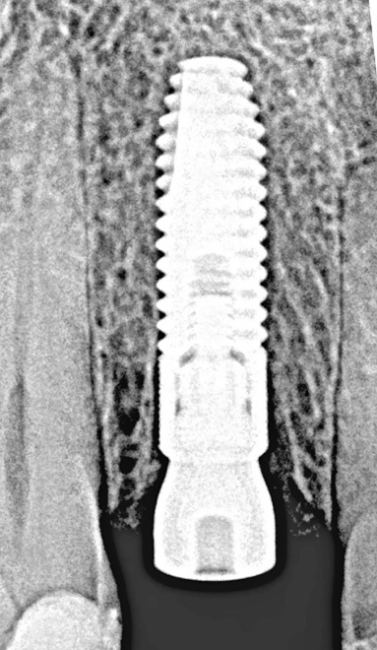
As the graft material is resorbed, and if normal bone fills the grafted site, it will be evident on the radiograph. As the graft material is resorbed, and if bone formation does not occur, a radiographic defect will be evident on the radiograph. You should know how long it takes to resorb the synthetic graft material you are using so you can understand when the graft material is gone and bone has formed. Cadaver bone graft granules are never fully resorbed and do not produce integration; however, they produce great looking radiographs, but do not support the implant.
As long as the graft is in place and no pathogens are present, this is definitely an improvement over no grafting, but these grafts have been shown to breakdown over time. This is a long and wordy explanation as to why we chose an immediate implant for #7 and an early implant for tooth #10.
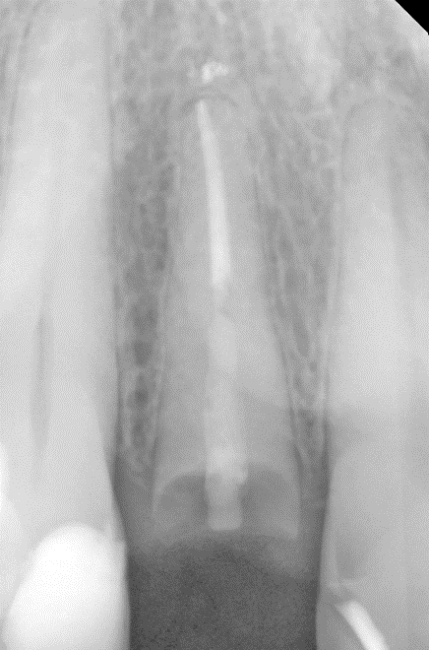
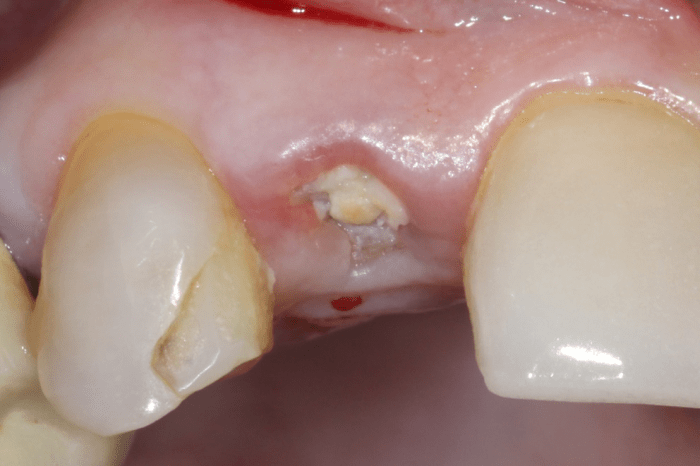
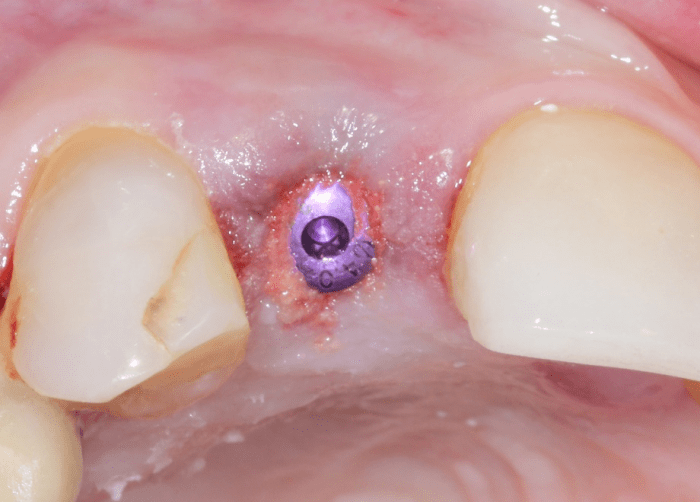
Tooth #7 had an intact socket. The defects around the immediate implant should be able to acquire the needed regenerative cells from the adjacent bony septum to resorb the graft material and fill the defect with normal bone.
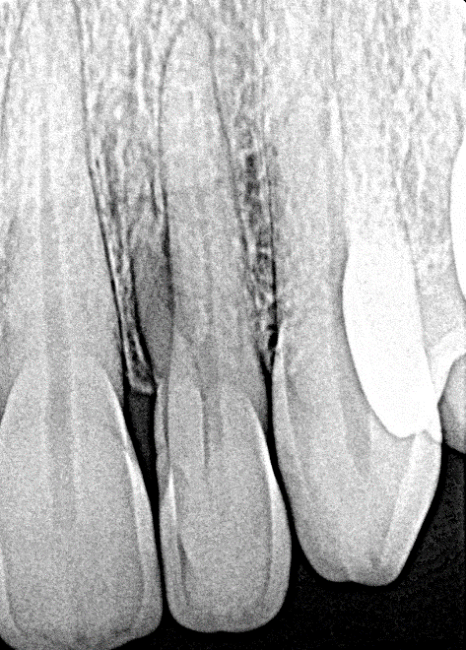
For #10, however, due to the furcation involvement on the second root and periodontal abscess, it is questionable whether it would have enough regenerative cells to fill the defect and integrate to an immediate implant.
A benefit of the early implant technique is that after one month, regenerative cells migrate into the coronal portion of the socket. When the implant is placed, it is surrounded by bone regenerative cells that can fill a coronal defect.
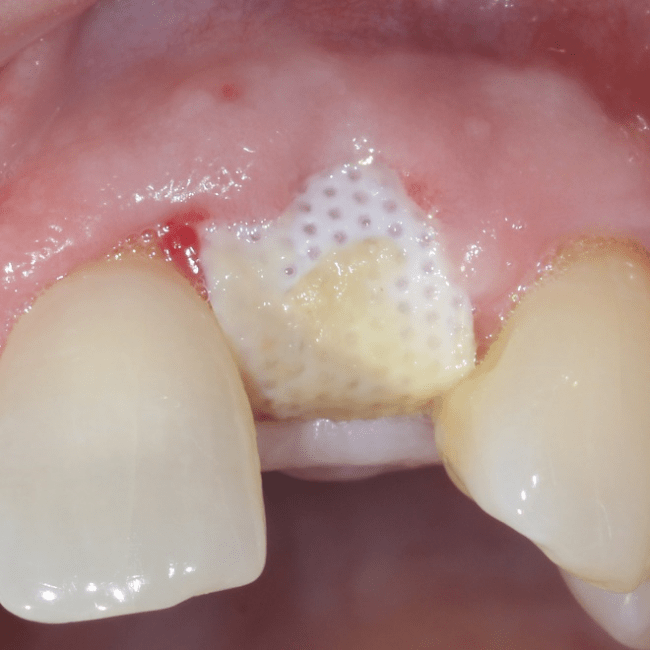
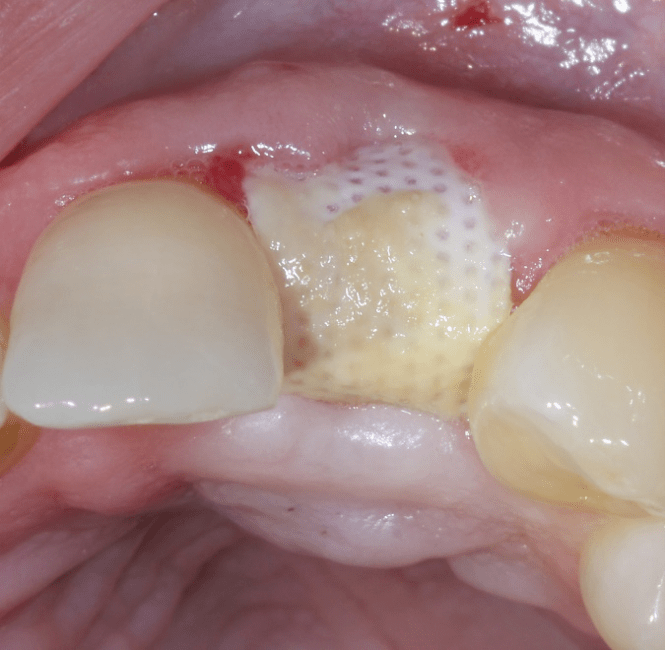
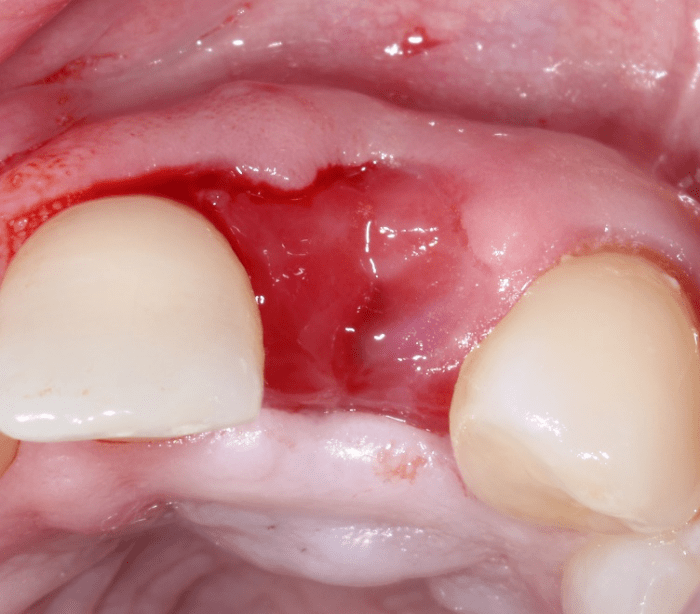
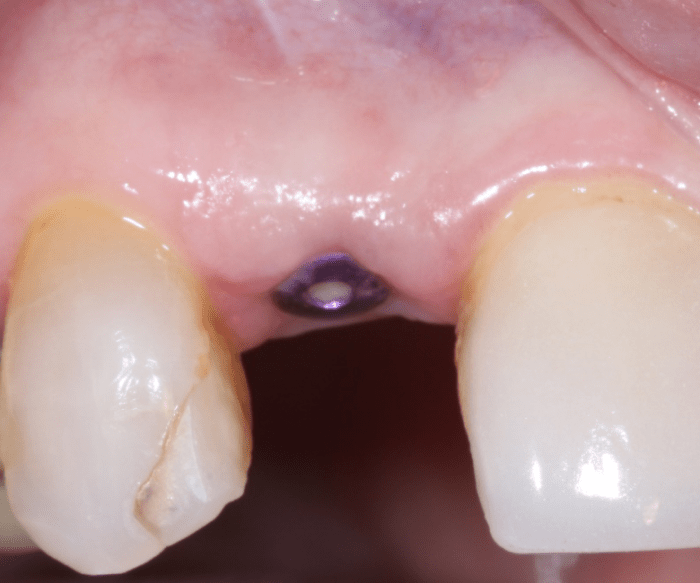
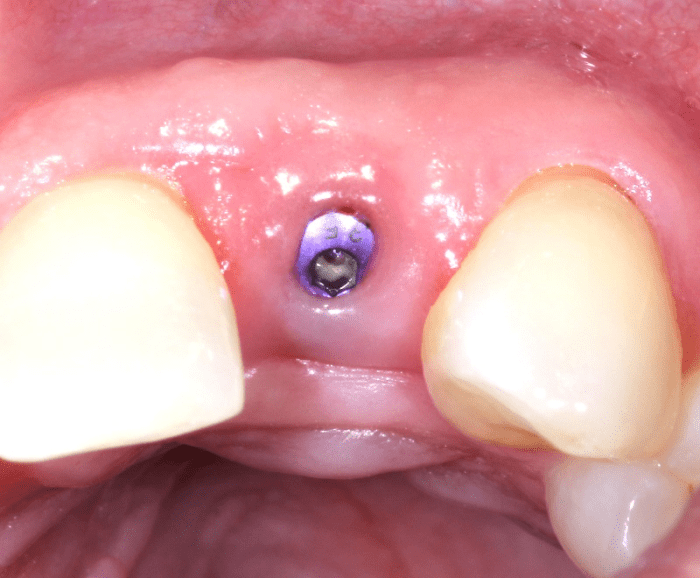
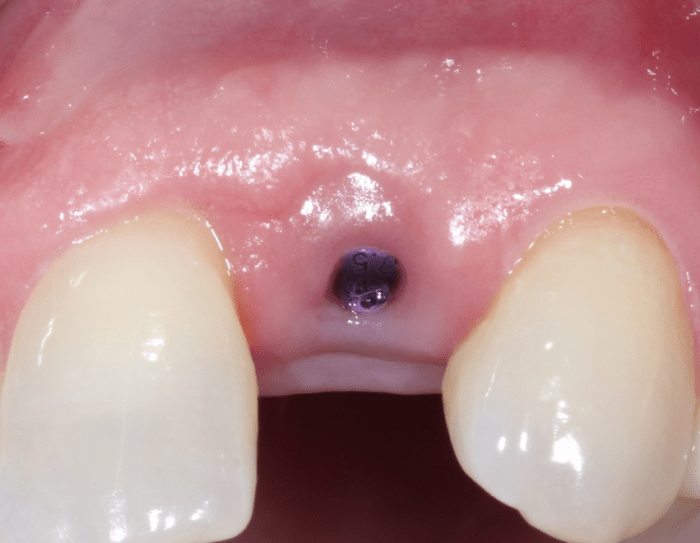
Let’s now review the early implant case for tooth #10.