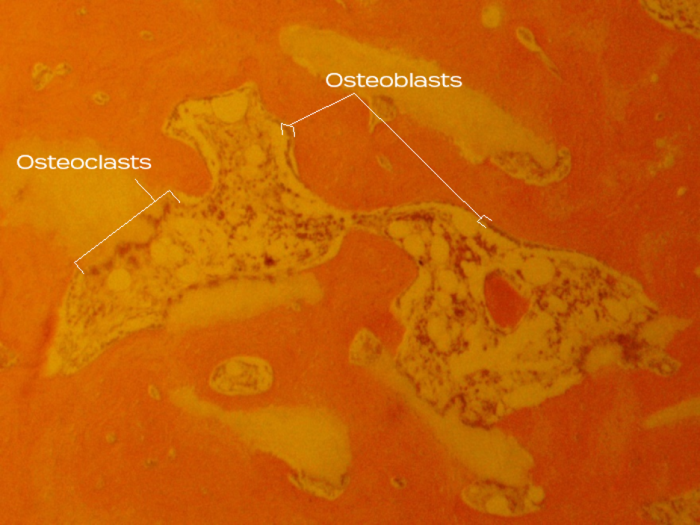
The predictability of the surgical procedure is a result of the regenerative potential of the graft material. However, equally important is that the material is a modern, science-based, FDA-cleared graft material and as such does not elicit an immune response by the host. By eliminating the host immune response, the material can be expected to perform consistently in each of your patients. By comparison, cadaver material interacts directly with the host’s immune system to produce calcification. Because there is no tissue matching or anti-rejection medication, it is not possible to predict success or failure when using transplanted materials. When evaluating histology of cadaver bone grafts, authors routinely state that little or no inflammation was found. They conclude that the cadaver material does not cause an inflammatory response. This is quite humorous. We all have patients struggling with autoimmune diseases where the patient’s own immune system is attacking itself. Do the authors expect us to believe that someone else’s bone will not elicit an immune response? The reason our profession thinks that cadaver bone does not elicit an immune response in our patients is because they are always looking at fully calcified histology and they have never seen histology of a cadaver graft prior to calcification.
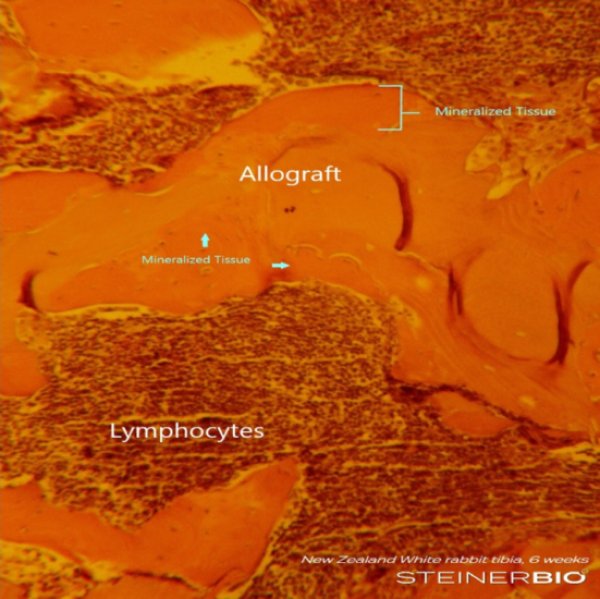
To emphasize this point, histology from the same animal at the same time frame makes this point clear. The following freeze-dried bone allograft histology shows a complete population of the graft site with chronic inflammatory lymphocytes. The histology of our putty mixed with our beta tricalcium phosphate granules shows no inflammatory response. The purpose of the body calcifying cadaver bone graft is to isolate it from the immune system and when this occurs the inflammation is reduced. Because no effort is made to predict how the host will respond to the cadaver tissue, there is no way to predict the outcome of the surgery when using those materials.